To Buy Cephalexin Online Visit Our Pharmacy ↓
 Drug Interactions to Watch with Cephalexin
Antibiotics to Avoid or Monitor with Cephalexin
Combining cephalexin with bacteriostatic antibiotics such as tetracyclines or chloramphenicol can theoretically reduce bacterial killing; clinicians should avoid routine pairing and weigh therapy goals and prioritize culture directed therapy to preserve efficacy.
Pairs that risk renal or auditory harm—aminoglycosides, vancomycin—require monitoring of creatinine and dosing, particularly if patients use OTC NSAIDs or change to Generics without counseling and monitor troughs.
Avoid redundant broad‑spectrum overlap with fluoroquinolones or macrolides to limit resistance; consult a Pharm Tech or pharmacist for review and adjust promptly when interactions are suspected.
| Monitor | Reason |
|---|---|
| Aminoglycosides | Nephrotoxicity |
Acid-reducing Drugs Affecting Cephalexin Absorption and Dosing
When patients reach for antacids or start acid-suppressing OTC therapy, absorption can feel like a bedside mystery. For cephalexin in particular, modest pH changes usually do not dramatically reduce bioavailability, but delayed gastric emptying or high-dose proton pump inhibitors might alter timing and peak levels.
Clinicians should review the patient’s meds—ask about antacids, H2 blockers, and PPIs—and consider holding or spacing doses. A simple Sig such as taking cephalexin two hours before or after an antacid often preserves exposure without changing the Script.
In renal impairment or persistent absorption concerns, counsel patients and involve a Pharm Tech or pharmacist for Meds Check. Therapeutic drug monitoring isn’t routine for cephalexin, but adjust dose by creatinine clearance.
Probenecid Raises Cephalexin Levels: Risks and Benefits
Adding probenecid to cephalexin slows renal excretion and raises antibiotic levels, which can extend coverage and allow less frequent dosing in select infections. Clinicians sometimes use this deliberately for difficult-to-treat cases, but it’s not routine for uncomplicated infections.
Higher cephalexin concentrations may increase adverse effects — nausea, diarrhea, and in rare cases neurotoxicity, especially with reduced kidney function. Patients on multiple drugs need careful review because altered levels can change efficacy or toxicity.
Before changing an Rx, discuss benefits versus risks with your prescriber and verify dosing with a Pharm Tech or pharmacist; monitor renal function and consider dose adjustment or avoidance if renal impairment or interacting medications are present and document in the chart.
Anticoagulants and Cephalexin: Bleeding Risk Considerations
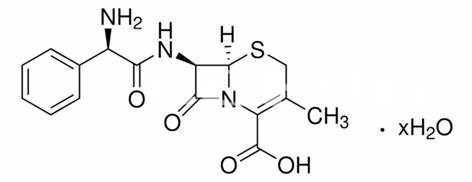
At the pharmacy a patient picking up cephalexin and a chronic blood thinner hears a brief warning: antibiotics can change bleeding risk. While cephalexin has limited interaction with warfarin compared with some cephalosporins, clinicians still advise caution and communication with the prescriber and pharmacist for clear Sig details.
Mechanisms include alteration of gut flora reducing vitamin K production and pharmacodynamic overlap that may potentiate anticoagulation. For patients on warfarin, direct oral anticoagulants, or heparins, check baseline INR or relevant labs, watch for bruising or unusual bleeding, and report changes promptly. Medication reconciliation with the Pharm Tech or prescriber avoids surprises.
Adjustments are individualized: some patients need closer INR monitoring or temporary dose changes, others require no change. Never stop an anticoagulant without medical advice; instead document the Rx, note interactions, and schedule a follow-up so benefits outweigh risks and rationale.
Cephalexin and Hormonal Contraception: What's Recommended
Most evidence shows that cephalexin does not reduce the effectiveness of hormonal contraceptives, so routine contraceptive changes are unnecessary. True enzyme inducers such as rifampin, not beta lactam antibiotics, are the main concern. If you have severe vomiting or diarrhea within a few hours of dosing, also use backup contraception until absorption is reliable. Consider OTC emergency contraception or a clinician visit for a copper IUD if exposure is suspected promptly.
When in doubt, finish the antibiotic course and discuss temporary barrier methods with your provider. Pregnancy testing may be appropriate after missed contraception plus unprotected sex. Pharmacists or Pharm Tech can review your full medication list, check for interacting agents, and confirm dosing. Keep an up-to-date Rx list and ask for counseling at prescription pickup or during follow-up to reduce uncertainty and ensure safe contraception during treatment and care.
| Trigger | Recommended action |
|---|---|
| Severe GI upset after dosing | Use backup contraception; consider emergency contraception |
| Concurrent enzyme inducer (e.g., rifampin) | Discuss alternative contraception with prescriber |
Kidney Function, Drug Interactions, and Dosing Adjustments
When creatinine rises, a simple cephalexin course can become complex. Clinicians must weigh renal clearance, concurrent drugs that compete for excretion, and the patient’s pill burden. A quick consult with a Pharm Tech during medication reconciliation or a chart review prevents toxic accumulation and unsafe dosing.
Adjusting dose is like tuning an instrument: reduce dose or extend interval, track symptoms, and watch for additive toxicity with other renally cleared agents or over the counter supplements. Document changes on the prescription and counsel about toxicity signs; consider Generics when switching formulations.
